

The operating layer where the study follows real life.
A virtual research ecosystem, built phygital.
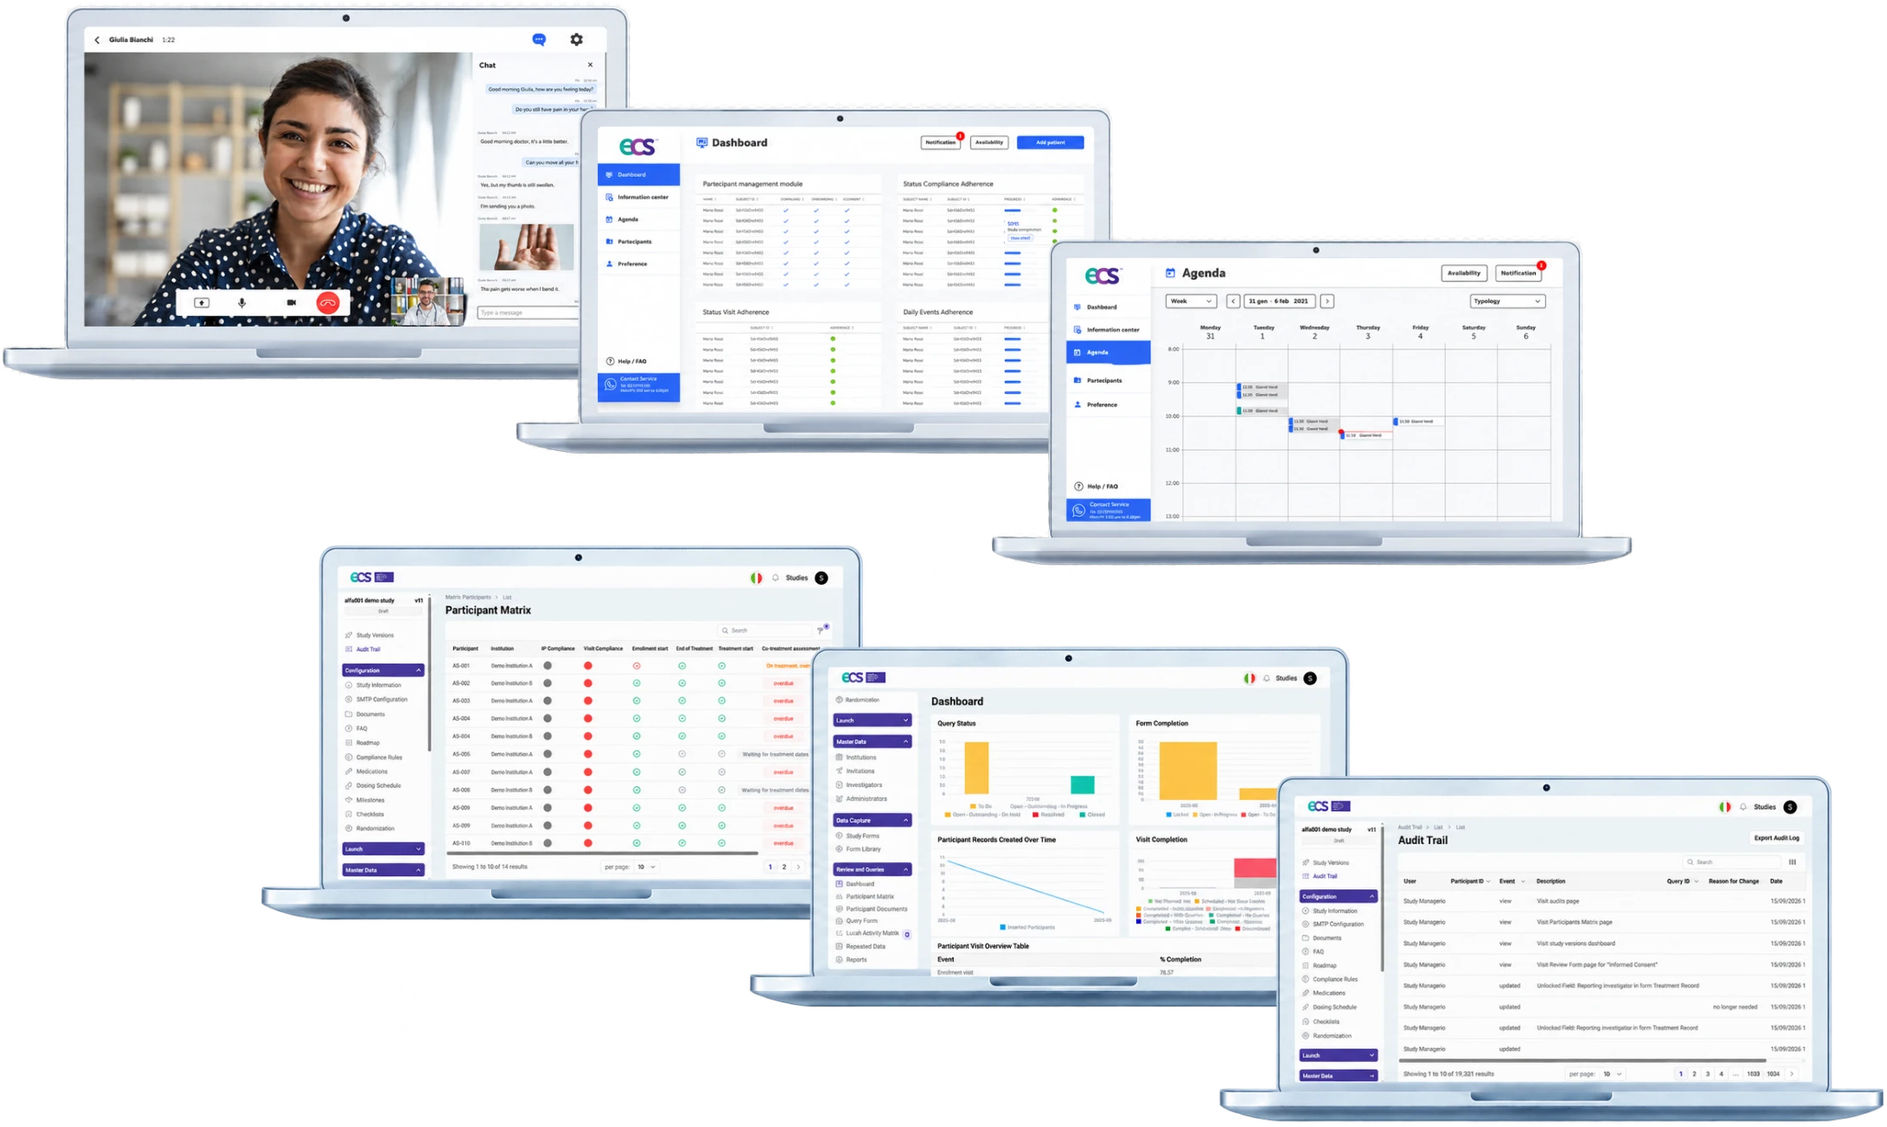
ECS®, the Evidence Capture System, runs a study end to end — from fully remote to hybrid, wherever the science calls for a physical touchpoint. Researchers, participants and sponsors work in the same environment, each seeing the study from their own seat.
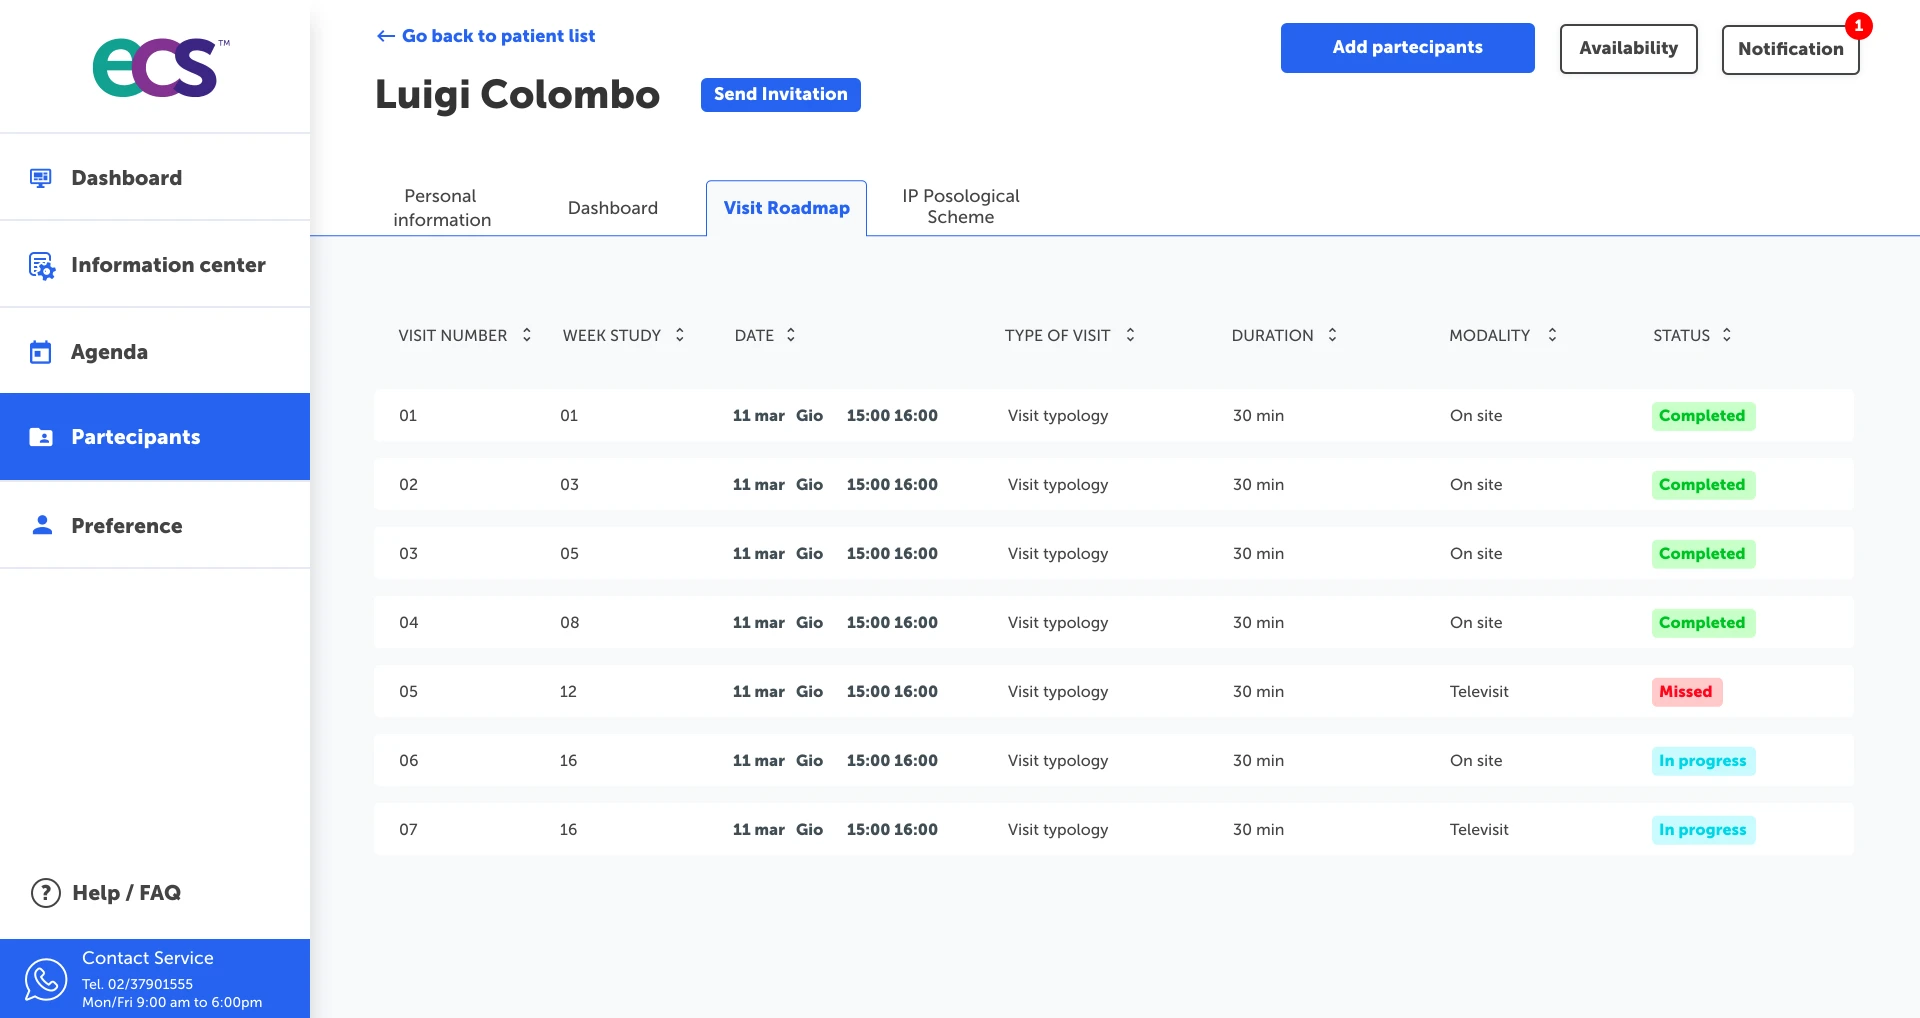
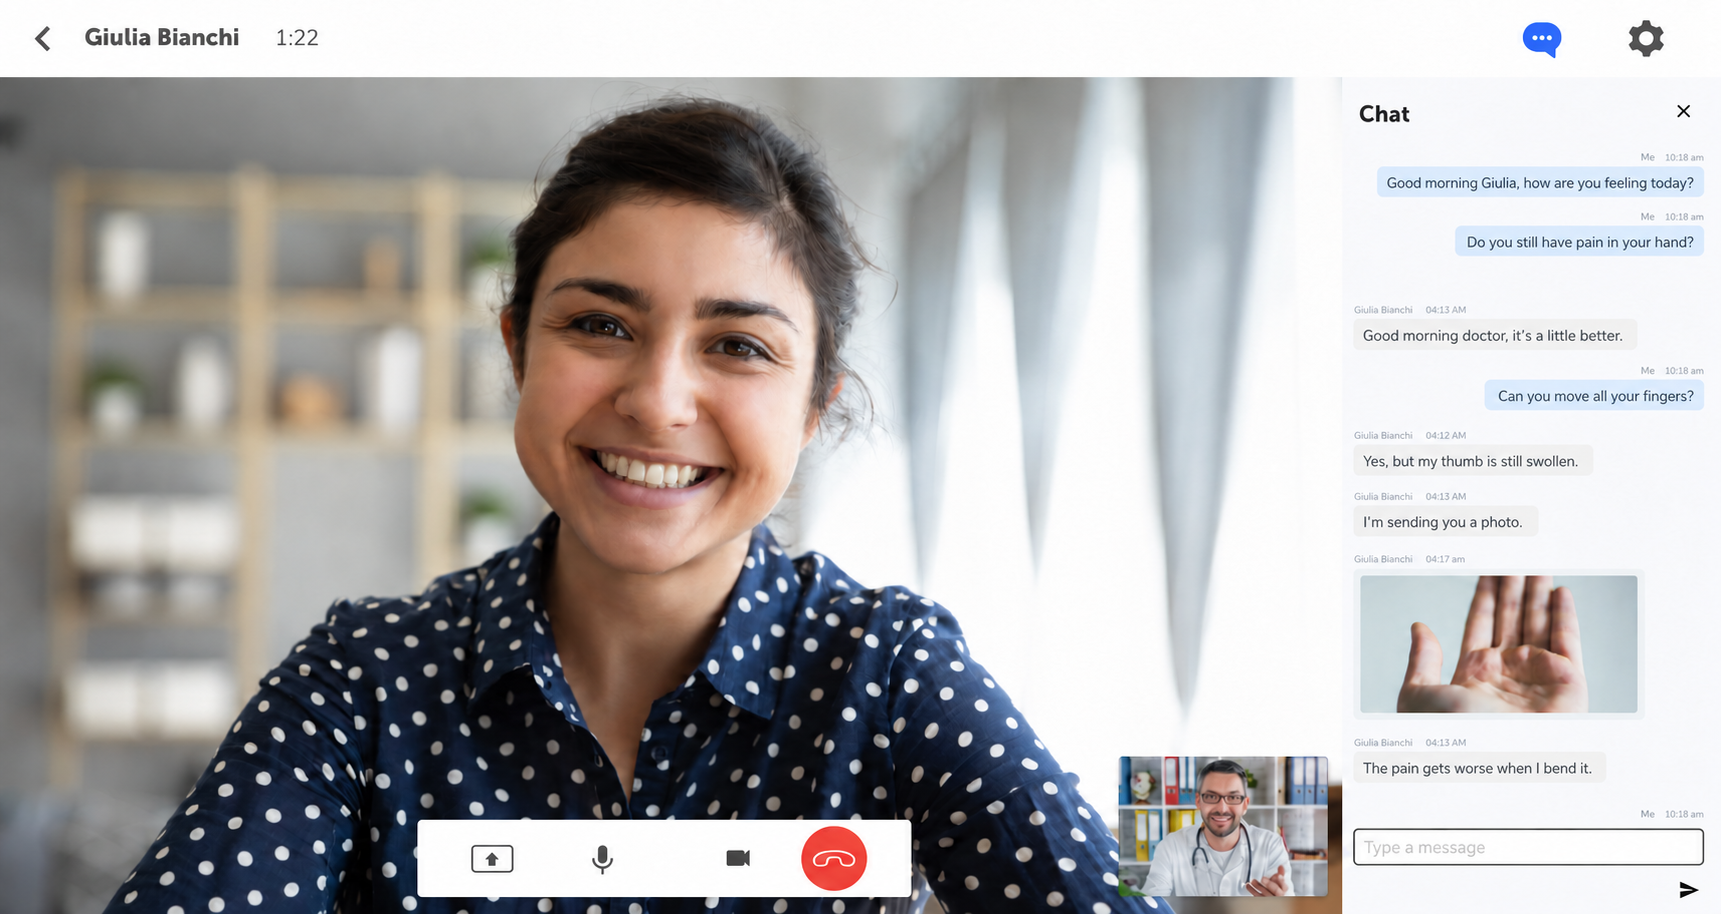
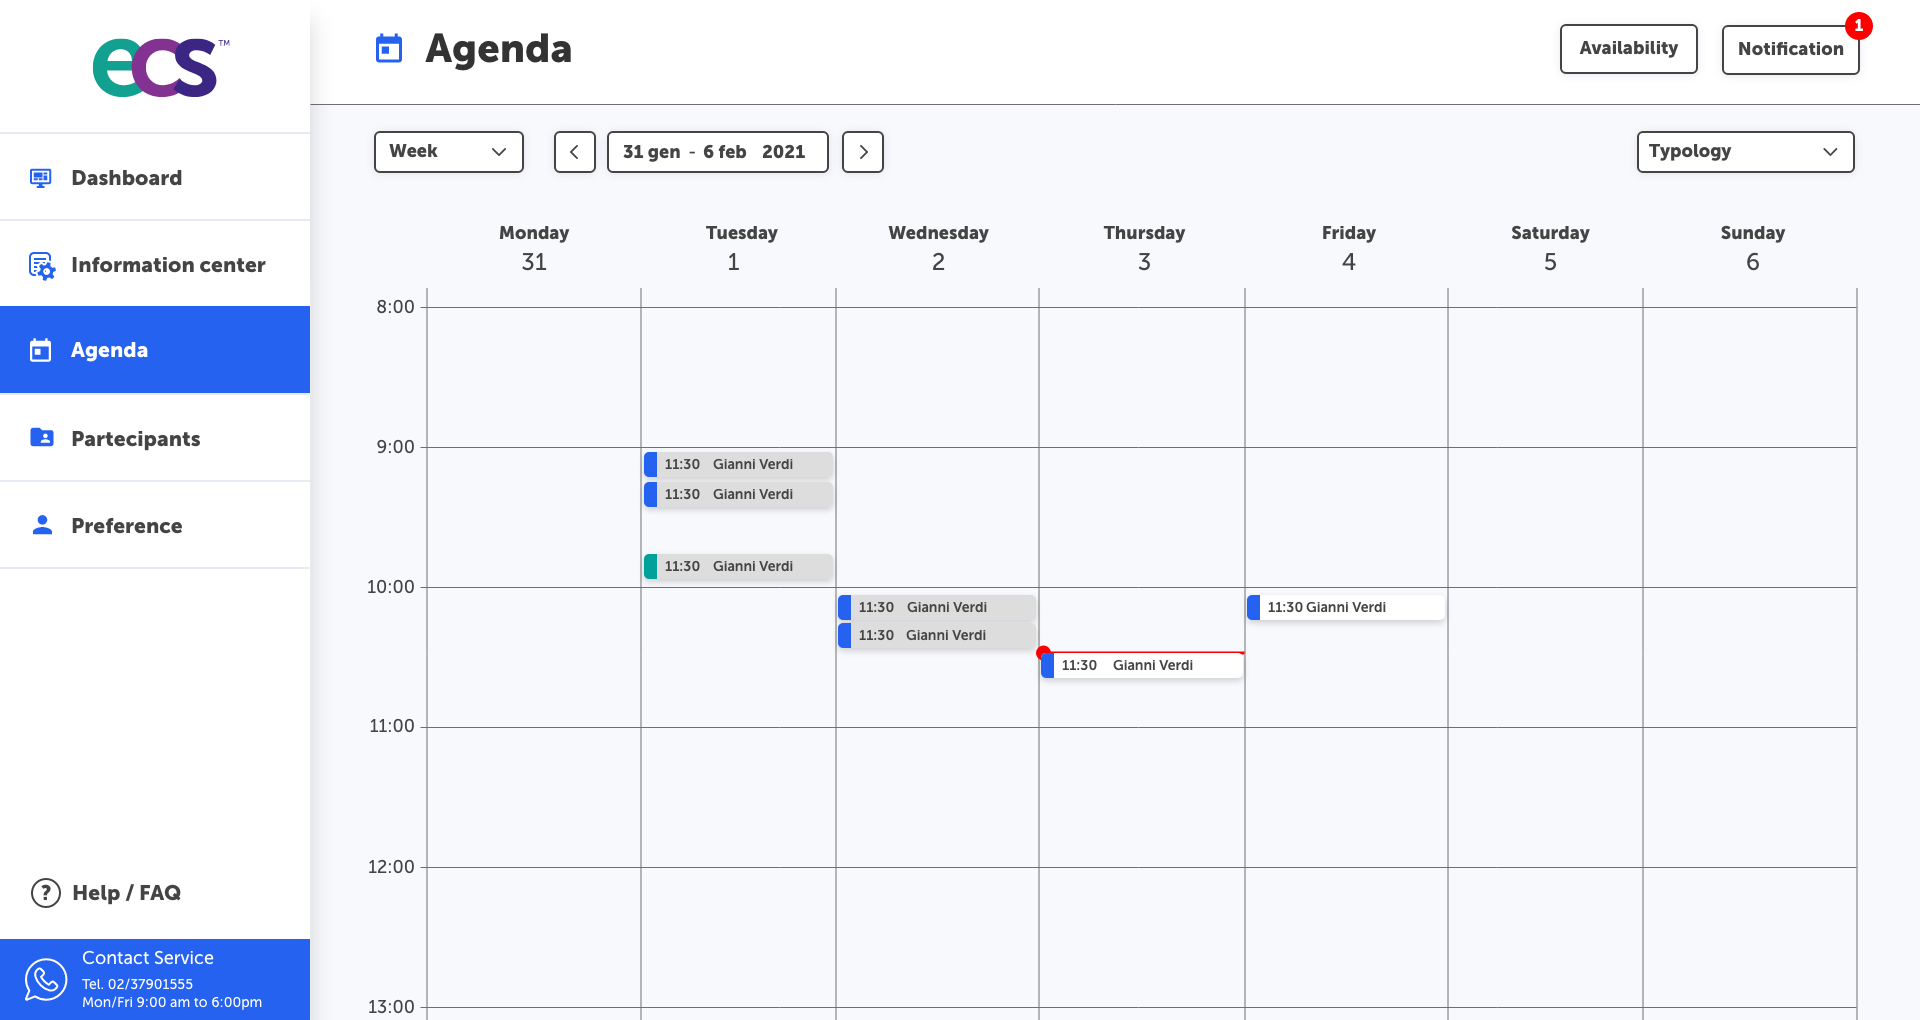
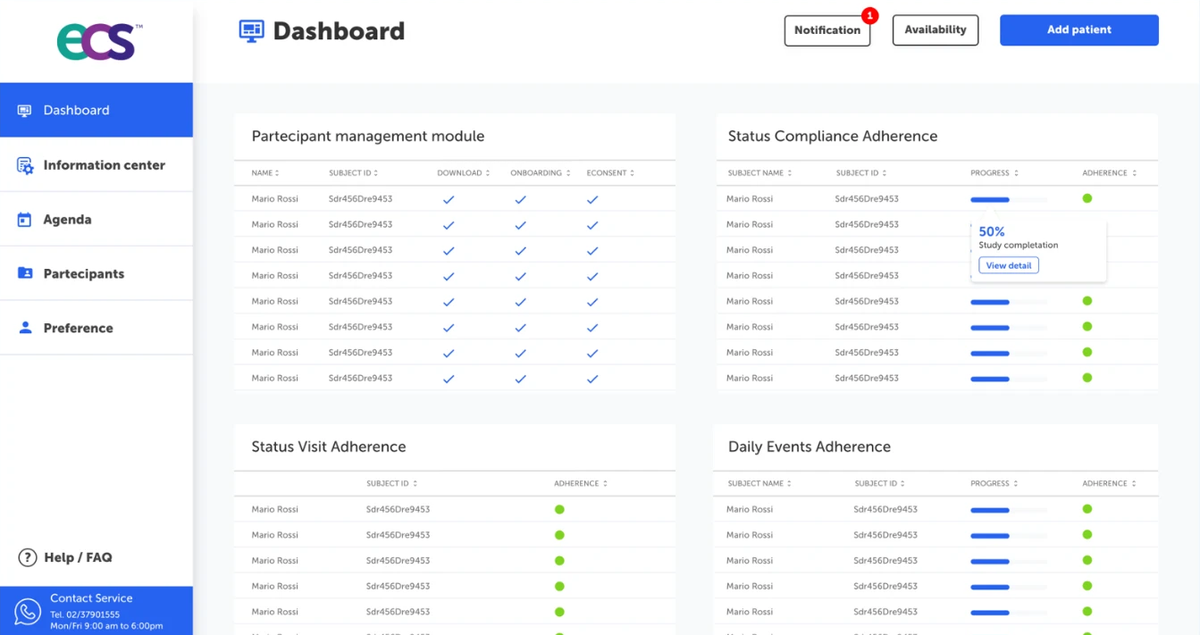



The guidance now describes the way we have been running studies.
We have been running studies this way from the start.
ICH E6(R3) asks for quality by design
Guidance now expects sponsors to design quality into the study rather than inspect it afterwards, which means the operating system of the study has to hold the design.
Regulators recognise decentralised elements
The EMA recommendation paper and the FDA final guidance describe televisits, home visits, direct-to-participant supply and remote data capture as normal parts of a trial.
The participant is where the data starts
Outcomes, adherence and device signals originate in daily life. A platform built around the site records them second-hand; one built around the participant records them at the source.
Beyond EDC. Beyond a stack of tools.
Three ways ECS® diverges from the categories sponsors usually compare it to.
EDCs assume a site visit happens and then gets transcribed. ECS® captures at the source, participant, device, home nurse, and lets the CRF assemble itself, so the work that usually waits for the end of a study happens during it.
Televisit, ePRO, consent, logistics and monitoring share one identity, one consent spine, one audit trail, ready to run as delivered.
Years of our founding team's direct-to-participant studies embedded in the product, matured well ahead of today's EMA/FDA guidelines.
What sets ECS® apart
An easy-to-use system is methodologically superior. Co-designed with clinicians, monitors and coordinators, ECS® reduces human error because it adapts to people's lives, not the other way around.
Research must not be a burden for the physician. We automate the digital translation of clinical data, fewer clicks, fewer manual reconciliations, more time given back to care.
We bring the trial to where life happens. From community pharmacies to primary and community care and the participant's home, every touchpoint becomes a source of high-quality real-world evidence.
Turn on only the layers a protocol needs, from simple electronic data capture to a multinational hybrid decentralised trial. Fully remote, fully centralised or anywhere in between, same platform, same audit trail.
Arms and cohorts opened or closed, treatment switches, dose escalation, amendments and re-consent handled while the study runs: forms, randomisation, supply and participant tasks reconfigure together, on one continuous audit trail. Built for real-world, adaptive and seamless designs.
AI in ECS® works as a quality guarantor. ViSA surfaces signals early, traceable and explainable, with human oversight at every step.
ICH E6(R3), 21 CFR Part 11, GDPR, ISO 27001 and CDISC built into every layer, with HL7 FHIR and REST APIs so ECS® plays well with the systems a sponsor already runs.
Evidence, sooner.
against site-only recruitment.
across our hybrid studies.
across hybrid and decentralised programmes.
a configuration proposal within 60 days of a protocol synopsis.
Evidilya programme data, hybrid and decentralised studies, 2019 – 2026. Indicative, every study differs.
One connected ecosystem, patients, clinicians, sponsors.
Participants, caregivers, investigators and sponsors meet on one operating layer, and the study is configured on top of it rather than assembled from separate tools.
Read it top to bottom: sponsors set the study, participants at home (left) and care teams at sites (right) meet in the middle on ECS®, and the operations and integration layers below carry the physical world and the data out. Arrows show what flows in each direction.


EDC and industry standards plug in as integrations.
Adaptive designs, treatment switches and amendments are absorbed while the study runs.
Finding, consenting and keeping the people the protocol needs. Powered by PHYGITAL-CROWD.
See how PHYGITAL-CROWD works →


Running the visit schedule and watching the study while it happens.
Turning what happens to a participant into regulatory-grade data.
Moving product, samples and people so a remote visit can actually take place.
Proving, at any moment, that the study was run the way it was written.
Evidence Engine
Reads across every layer and turns what the study collects into analysis-ready evidence, with the lineage of each figure kept intact.
Armonia
Keeps the patient community close to the study, so participants stay in contact with the programme beyond the visit schedule.
Studies that come to the participant, wherever they are.
Recruited, consented, dosed, monitored and retained on ECS®, at home, in the community, in a pharmacy or at a hospital. Decentralised trials, done to ICH E6(R3).
One journey, from eRecruitment to close-out, orchestrated on ECS®, experienced through LucaH®, the participant app.
One ecosystem, one participant, from first contact to published result.
From awareness to publication, every step of the Direct-to-Participant journey runs on ECS®, with a human study team in the loop.
- 01
Awareness
Ethical, on-brand recruitment. Digital reach, community HCPs, patient advocacy.
- 02
Consent
Multi-language eConsent with legally-valid signatures, audit-trailed on ECS®.
- 03
Prescreening & screening
Prescreening runs upstream of ECS®; screening happens on ECS®, hospitals, community HCPs, pharmacies, home. One ecosystem, one source of truth.
- 04
Data capture
ePRO, eCOA, wearables, home visits, telehealth. Whatever the endpoint asks for, captured on-model, GxP.
- 05
Interaction
Study-team messaging, reminders, home logistics. Human touch on top of digital rails.
- 06
Retention
Participant portal with progress, benefits, results. Retention is a design outcome.
- 07
Publication
Dossier, publication, market access. The arc closes where the participant's contribution matters most, evidence.
Pick a prescribed treatment. See the journey reconfigure.
A small illustrative preview of how ECS® adapts visit cadence, ePRO frequency, safety monitoring and re-routing rules to the therapy actually prescribed. Fully keyboard-navigable, use ← → to move between treatments.
- Visit cadence
- Baseline · remote check-ins at week 2, 6, 12 · quarterly televisit thereafter.
- ePRO frequency
- Daily short diary for the first 14 days, then weekly symptom & adherence ePRO.
- Safety monitoring
- Monthly self-reported tolerability review; lab uploads on the participant's routine schedule.
- Adaptive triggers
- Two missed doses in 7 days → nurse outreach within 48h and adherence coaching module.
In production, ECS® derives these parameters from the prescription captured at baseline and updates them on any dose change, switch or discontinuation, with full audit trail.
Same ecosystem, three points of view.
Evidence on time, with oversight you can defend.
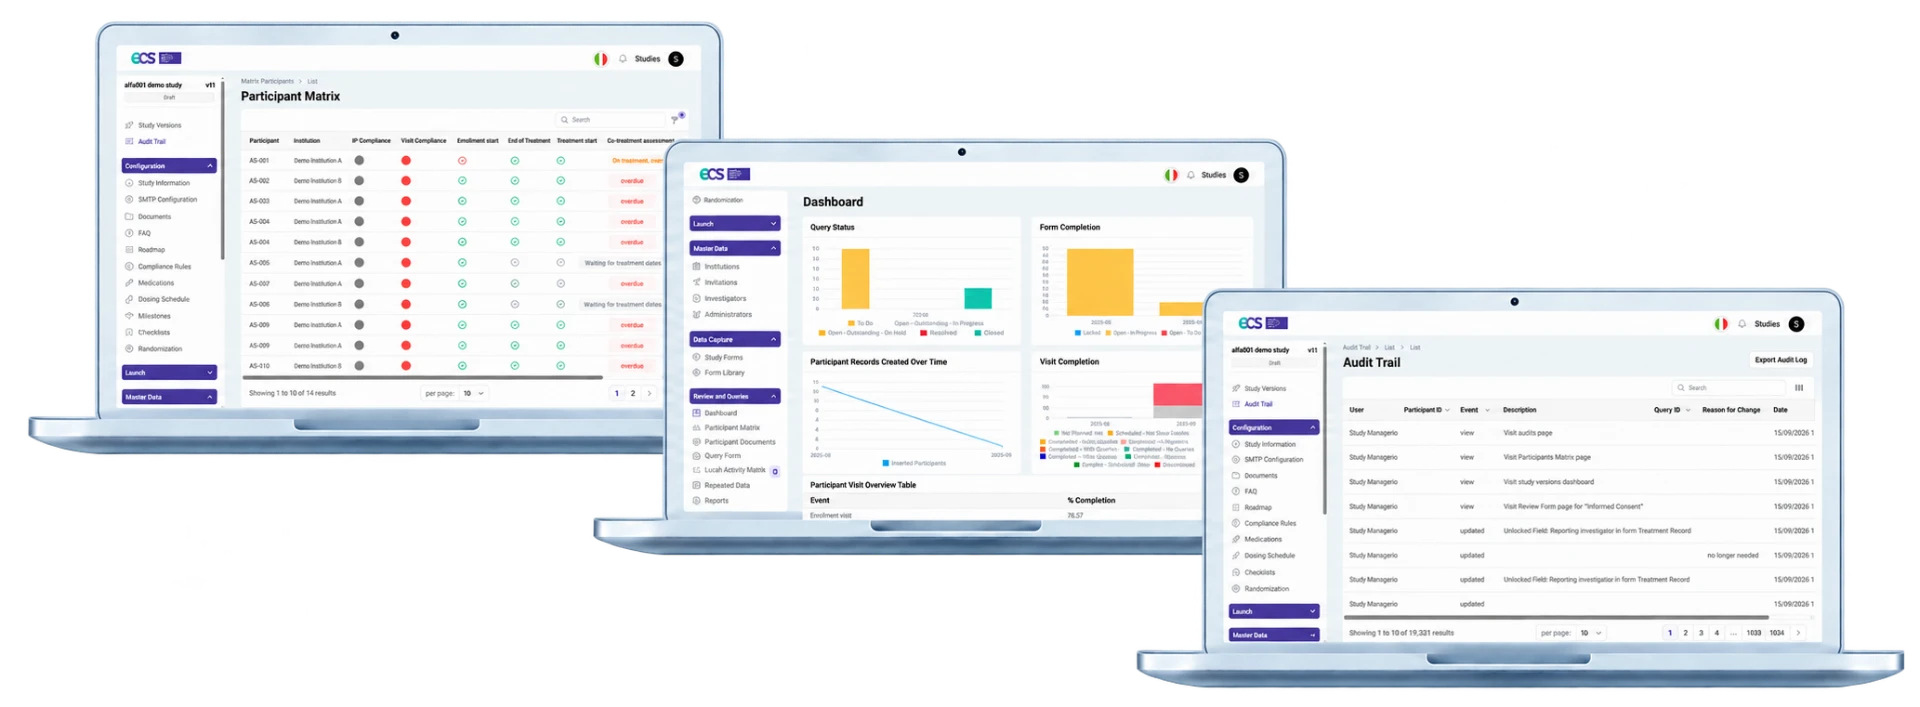
Modular activation, centralised monitoring and analysis-ready exports, from first-patient-in to publication, without slowing execution.
- Centralised, hybrid and fully virtual designs on one contract and one ecosystem.
- Real-time visibility on recruitment, quality and safety, no overnight extracts.
- Recruitment designed around where participants already are, and retention that holds because of it.
- Automated workflows that cut admin burden across countries and vendors.
- Analysis-ready outputs, SDTM / ADaM, straight into biostatistics.
Less admin, more clinical time.
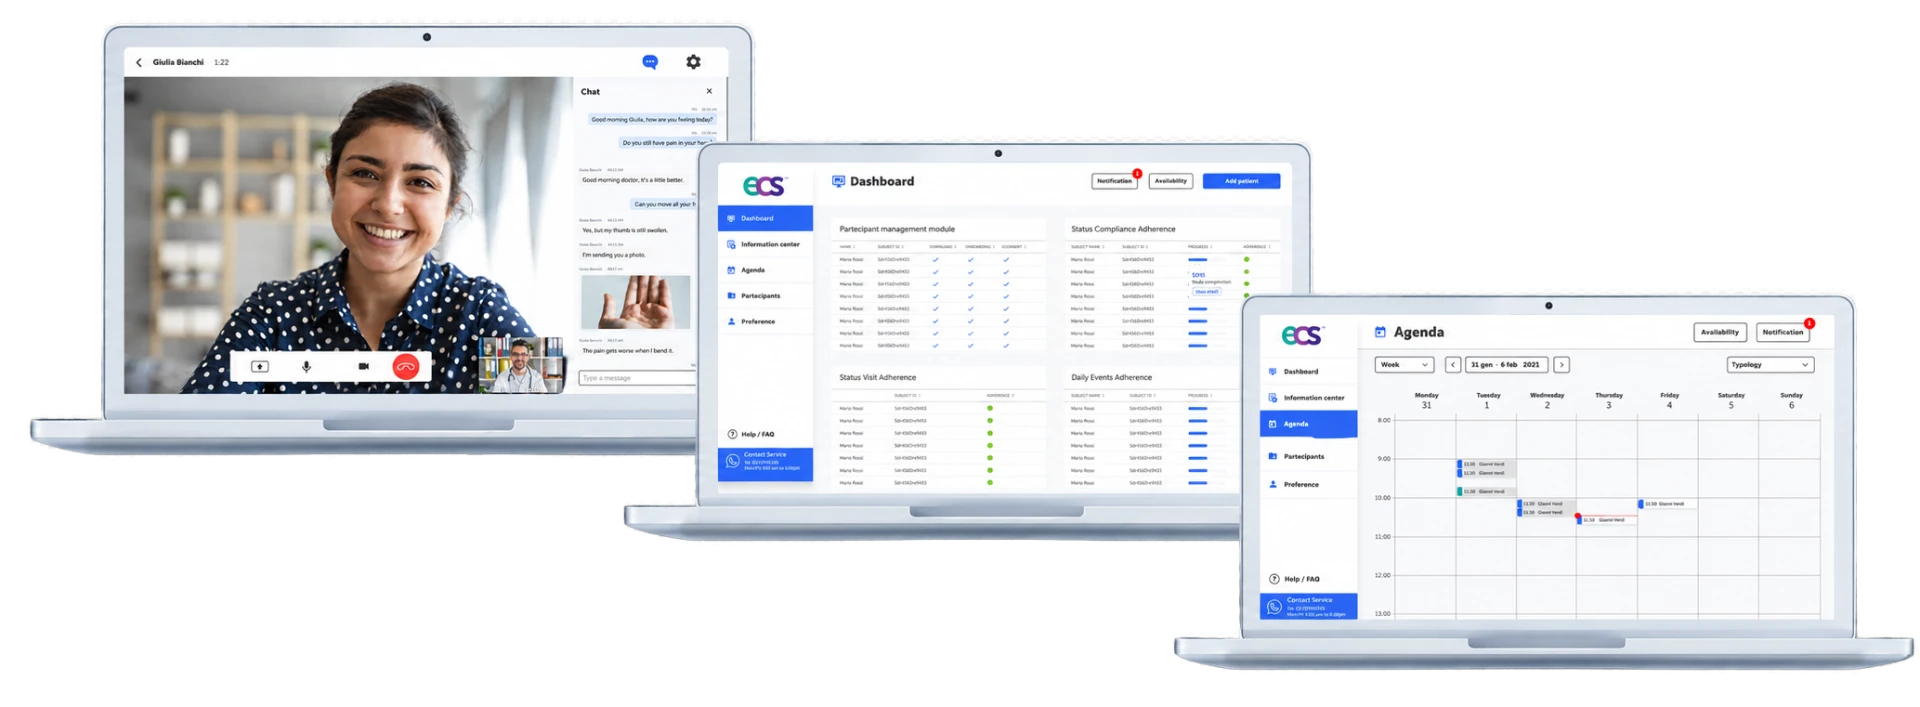
One cockpit for televisit, source data, queries and e-signatures, co-designed with the clinicians, monitors and coordinators who use it every day.
- Co-designed with healthcare professionals to match real clinical workflows.
- Fits routine practice, in hospital, community care or remote settings.
- Source captured once, reused across CRF, monitoring and export.
- Fewer manual reconciliations, fewer disruptions to care.
- AI support that surfaces what needs attention, never decides for you.
The study comes to you.
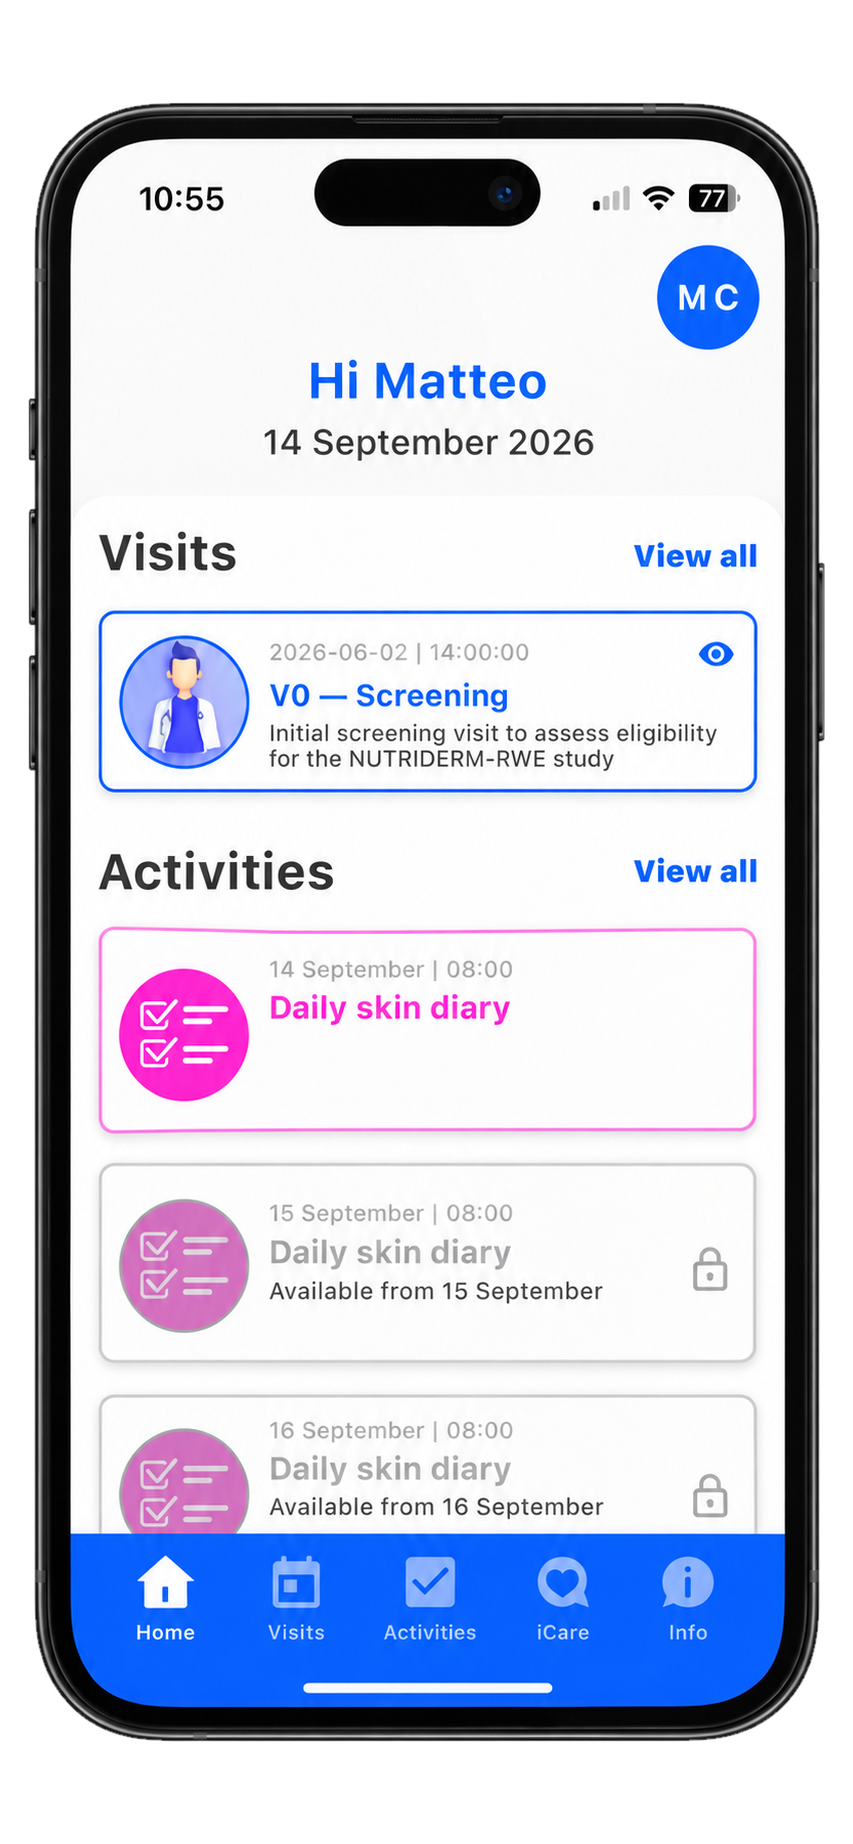
Through LucaH®, participants get clear instructions, telehealth visits, symptom diaries and reminders, on their own device, at their own pace.
- One app for consent, tasks, visits and reminders.
- Fewer site visits, more time to live.
- Plain-language content, translated and accessible.
- Transparent data use, always aligned with consent.
- Support just a tap away, caregivers and proxies included.
Built for evidence-grade trust from day one.
Deployed on regional AWS infrastructure, with data residency in the sponsor's jurisdiction.
Send us the protocol. We will show you the configuration.
Share a synopsis and we come back with the ECS® build for your design.